New Food Pyramid 2026: A Game-Changing Shift in Dietary Guidelines
In early 2026, the nutrition world witnessed a seismic shift. The US Department of Health and Human Services, alongside the Department of Agriculture, released the Dietary Guidelines for Americans 2025-2030 - and it's nothing short of revolutionary.
Passionate about writing and a graduate in clinical dietetics. She is particularly interested in phytotherapy and the effects of ketogenic nutrition on cognitive brain function.
Graduate in dietetics. She is interested in the ketogenic diet and its effects. She is responsible for content creation and content verification on the website.
The USDA has officially recognised the ketogenic diet as an equal dietary strategy for people with metabolic conditions – the most significant shift in official nutritional guidance in fifty years. [1]
On 7 January 2026, the US Department of Health and Human Services (HHS) and the Department of Agriculture (USDA) published a document that fundamentally transforms official nutrition science. The five key changes at a glance:
3 equal macronutrient models – including a ketogenic model with 5–20% of energy from carbohydrates
Grains demoted from the dietary foundation to tier 4 of the hierarchy
Added sugar limit reduced from 10% to 6% of daily energy (max. 25–30g/day)
First official recognition that eliminating grains may benefit people with metabolic conditions
End of the one-size-fits-all approach – replaced by individualisation based on metabolic status
People with insulin resistance, type 2 diabetes or metabolic syndrome now have an official institutional basis for drastically reducing carbohydrates for the first time. [1]
UK vs USA: NHS Eatwell Guide vs USDA 2026
While the USA implements a paradigm shift with Dietary Guidelines 2025–2030, the UK’s NHS Eatwell Guide – last updated in 2016 and still the official government nutrition tool – takes a considerably different approach.
Feature
USDA 2025–2030 (USA)
NHS Eatwell Guide (UK)
Carbohydrates
3 models: 5–55% of energy
Starchy foods should make up just over a third of diet
Fats
25–75% depending on model
Small amounts only; unsaturated fats preferred
Grains
Tier 4 – optional for metabolically ill
Base every meal around starchy carbohydrates
Low-carb / keto
Officially recommended for at-risk groups
Not included in standard recommendations
Saturated fats
Rehabilitated in natural sources
Limit – linked to raised cholesterol
Added sugar limit
Max. 6% of daily energy
Max. 5% of daily energy (SACN 2015)
Full-fat dairy
Accepted in dietary patterns
Lower-fat options recommended
Target population
Healthy + metabolically ill adults
General healthy population
A critical difference: the NHS Eatwell Guide is designed for the general healthy population and advises anyone with special dietary requirements or medical needs to consult a registered dietitian for individual adaptation. The USDA guidelines include metabolically ill people directly and give them clear, official recommendations for the first time.
A notable point of convergence: both the UK and USA now treat fruit juices as a source of free sugars comparable to sugary drinks – the NHS limits juice to 150ml per day, while the USDA 2026 classifies all juices alongside sugar-sweetened beverages. The directions are similar – the pace of change differs considerably.
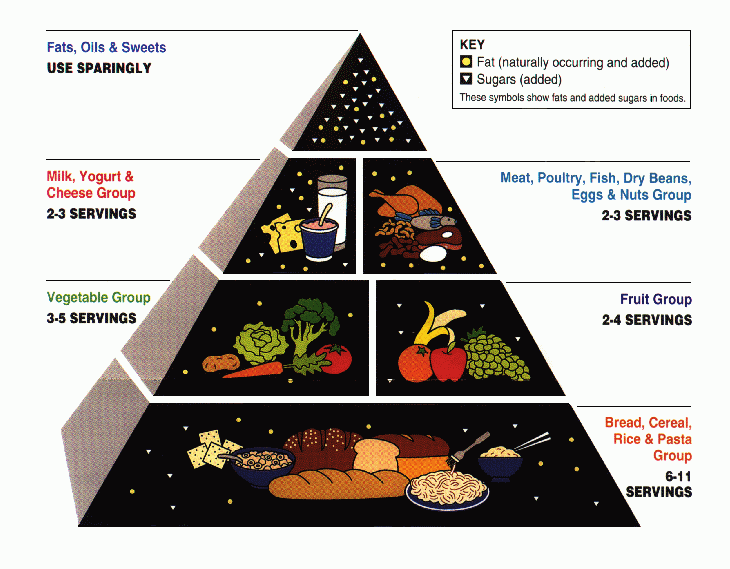
The original USDA food pyramid, from 1992 to 2005
USDA food pyramid from 2005–2011, MyPyramid
Was the Pyramid Actually Inverted?
Yes – for people with metabolic conditions, complete elimination of grains is now officially permitted for the first time in history. The new guidelines don’t present a traditional pyramid in graphic form, but the USDA establishes a clear 5-tier hierarchy that inverts previous priorities.
Two important terms to distinguish:
Term
What it means
‘Inverted pyramid’
Metaphor: carbohydrates move up the hierarchy, fats form the foundation
‘Food hierarchy 2026’
New 5-tier model replacing the USDA pyramid (1992) and MyPlate (2011)
Practical consequence: in every previous model, grain products were obligatory and foundational. In the 2026 model, they can be completely eliminated for people with metabolic disorders – without breaching official recommendations.
For metabolically healthy people: the recommendations don’t change fundamentally – whole grains remain part of a balanced diet.
The New 5-Tier Hierarchy – Full Analysis
The USDA allows significant deviations for people with metabolic conditions for the first time. Each tier carries concrete recommendations on quantity and frequency.
Tier 1 – Foundation: Non-Starchy Vegetables and Quality Fats
MCT oils, extra virgin olive oil, coconut oil, butter and ghee, oily fish, avocado, nuts and seeds
Fats should make up 30–50% of daily energy intake
What to avoid:
Trans fats and industrially refined vegetable oils
Tier 1 Deep Dive: The Role of MCT Oils
Medium-chain triglycerides (MCTs) deserve special attention within Tier 1. Unlike long-chain fatty acids found in most foods, MCTs are rapidly absorbed and transported directly to the liver, where they are preferentially converted into ketones – making them uniquely efficient as fuel for the brain and muscles.
For anyone following the low-carb or ketogenic model recommended in the new USDA guidelines, MCT oils offer several practical advantages: they accelerate entry into ketosis, provide fast-releasing energy without a blood sugar spike, and are easily added to coffee, smoothies or salad dressings. Clinical research suggests MCT supplementation can increase ketone production by up to four times compared to dietary fat alone, making them a particularly valuable tool during metabolic adaptation.
Tier 2 – Quality Protein Sources
What to include:
Recommended intake: 1.2–2g of protein/kg of body weight per day
Fermented dairy products – optional (people with insulin resistance or PCOS may eliminate these)
What to limit:
Pulses moved to optional category
Tier 3 – Low-Glycaemic Fruit, Nuts and Seeds
Category
Recommendation
Berries (blueberries, raspberries, strawberries)
1–2 portions daily
Moderately sweet fruit (apples, pears, citrus)
max. 1 portion daily
High-sugar fruit (bananas, grapes, mango)
rarely or never
Fruit juice
classified as source of simple sugars = same as sugary drinks
Tier 4 – Grains and Starchy Vegetables (revolutionary change)
Group
Recommendation
Metabolically healthy people
max. 3–6 portions of whole grains daily
People with insulin resistance, type 2 diabetes, PCOS
max. 1–3 portions or complete elimination
Skipping this tier entirely
officially recognised for the first time as potentially health-beneficial
Tier 5 – To Eliminate: Added Sugars and Ultra-Processed Foods
What to concretely eliminate:
Sugary drinks, energy drinks, fruit juices
Industrial breakfast cereals and cereal bars
Biscuits, confectionery, fast food
Products containing high-fructose corn syrup
Warning: products labelled ‘light’, ‘diet’, ‘fitness’ or ‘fat-free’ – often contain more sugar than standard versions
New limit for added sugars: max. 6% of daily energy (previously 10%) = max. 25–30g sugar per day at 2,000 kcal.
Flexible Macronutrient Models: Three Equal Approaches
Model
For whom
Carbohydrates
Protein
Fat
Standard
Metabolically healthy people
45–55%
20–30%
25–35%
Moderately low-carb
Insulin resistance, prediabetes
25–40%
25–30%
35–45%
Low-carb and ketogenic
Type 2 diabetes, metabolic syndrome
5–20%
20–30%
50–75%
This is the first official endorsement of the ketogenic diet as an equal dietary strategy by the most important public health institution in the USA. [1] For people transitioning to the low-carb model, electrolytes – particularly sodium, potassium and magnesium – become especially important, as the body excretes more minerals when carbohydrate intake is reduced. Quality exogenous ketones can also support the metabolic transition during the first weeks.
Keto and the 2026 Pyramid: How They Align
The ketogenic diet – 20–50g of carbohydrates daily, 1.2–2g of protein/kg of body weight, 70–80% of energy from fat – fits the new paradigm more closely than any other dietary model currently in clinical use. [1]
2026 USDA principle
How keto delivers it
Quality fats as foundation
70–80% of calories from whole food fats
Minimal added sugars
Effectively zero in a well-formulated keto diet
Protein at 1.2–2g/kg
Standard keto protein recommendation
Grain elimination for metabolic conditions
Core keto principle since 1921
Nutrient density prioritised
Fatty fish, eggs, leafy greens – all keto staples
Over 500 clinical studies published in journals including The Lancet, NEJM and Diabetes Care confirm the effectiveness of this approach for reducing blood glucose, insulin resistance and body weight. [2] A meta-analysis in Nutrition & Metabolism (2024), analysing 29 clinical trials, documents significant reductions in fasting blood glucose (–11.68 mg/dl), HbA1c (–0.29%) and insulin resistance (HOMA-IR: –0.71) in patients following the ketogenic model. [2]
Research by Hallberg et al. (2018, Diabetes Therapy) demonstrates efficacy and safety comparable to pharmacological treatment in managing type 2 diabetes over one year. [3]
Want to explore ketosis symptoms and understand what happens during the metabolic shift? Our detailed guide covers everything from early signs to long-term adaptation.
Practical Guide: How to Apply the New Hierarchy
The new hierarchy is only useful if you know how to translate it into everyday meals. Here is a concrete three-step approach based on your metabolic profile.
Step 1: Know Your Metabolic Status
Before choosing a macronutrient model, you need to understand your starting point:
Orientation indicator: waist circumference (metabolic syndrome risk: men >94cm, women >80cm)
Optional: HOMA-IR index (calculating insulin resistance from fasting glucose and insulin)
Step 2: Choose the Right Model
Blood test result
Recommended model
All normal, healthy BMI
Standard model (45–55% carbohydrates)
Glucose at upper limit, overweight
Moderately low-carb (25–40%)
Prediabetes, insulin resistance, type 2 diabetes
Low-carb / ketogenic (5–20%)
Step 3: Build Your Meals Around the 5 Tiers
Daily template for the low-carb model (example for a 70kg person):
Breakfast:
3 eggs in butter + handful of spinach + half an avocado
Black coffee or tea, optionally with MCT oil
Lunch:
150g salmon or sardines + 200g broccoli or courgette with extra virgin olive oil
Handful of walnuts
Snack (optional):
Handful of blueberries or raspberries + 30g hard cheese
Dinner:
150–200g grass-fed meat or free-range poultry
200g leafy greens or other non-starchy vegetables with olive oil
Practical tips for the transition:
Find recipe inspiration in our keto recipes collection
In the first 2–4 weeks, expect adaptation symptoms (fatigue, headaches) – a natural response to the change in primary energy source, sometimes called the ‘keto flu’
Increase sodium intake (add sea salt to food or water) – the ketogenic diet increases electrolyte excretion via the kidneys
Track protein intake – minimum 1.2g/kg of body weight daily to preserve muscle mass
Measure ketosis – use urine or blood ketone tests to confirm entry into ketosis
What’s Next? Ketosis as the Next Step
The 2026 dietary guidelines create a solid foundation for low-carbohydrate eating – but that is only the starting point. If you want to understand how the body’s metabolic transformation unfolds after reducing carbohydrates, what ketosis symptoms to expect during the transition, and how to monitor it effectively – explore our detailed guide to this unique physiological state.
For everyday meal inspiration within the new framework, browse our keto recipes – all designed to fit the 2026 hierarchy’s Tier 1 and Tier 2 priorities.
FAQ: 5 Common Questions
Does the new 2026 food pyramid apply in the UK?
The Dietary Guidelines for Americans are official US guidelines. In the UK, the NHS Eatwell Guide remains the official government nutrition tool. However, US guidelines carry significant influence on international nutrition science and are widely cited in medical literature. The NHS advises anyone with metabolic conditions or special dietary needs to consult a registered dietitian for individual guidance.
Is the ketogenic diet now officially recommended?
Yes – for a specific group. The low-carb and ketogenic model (5–20% of energy from carbohydrates) is for the first time officially recommended for people with type 2 diabetes, metabolic syndrome and significant insulin resistance. [1]
Have grains been completely removed from recommendations?
No. For metabolically healthy people, 3–6 portions of whole grains daily remain recommended. The change applies to people with metabolic conditions – for them, complete elimination is officially permitted for the first time.
What does the 6% added sugar limit mean in practice?
At 2,000 kcal per day, this equals a maximum of 120 kcal – approximately 25–30g of sugar daily. The previous limit was 10% (around 50g). This new limit effectively excludes daily consumption of sweets, fruit juice and sugary drinks. The NHS already recommends limiting free sugars to no more than 5% of energy intake under SACN 2015 guidance – the USDA has now aligned more closely with this stricter threshold.
Are saturated fats now fully ‘rehabilitated’?
The guidelines shift the emphasis from the chemical structure of fat to its origin and quality. Trans fats remain to be eliminated. Saturated fats from natural sources (butter, grass-fed meat, coconut) are evaluated in the context of the overall dietary pattern – not in isolation. This represents a significant departure from the NHS Eatwell Guide, which still recommends limiting saturated fat and choosing lower-fat dairy products.
Bilbiography
View all
U.S. Department of Agriculture and U.S. Department of Health and Human Services. Dietary Guidelines for Americans, 2025-2030. December 2024. dietaryguidelines.gov
Hallberg, S. J. et al. (2018). Effectiveness and safety of a novel care model for the management of type 2 diabetes. Diabetes Therapy, 9(2), 583-612. Bueno, N. B. et al. (2013).
Very-low-carbohydrate ketogenic diet v. low-fat diet for long-term weight loss: a meta-analysis of randomised controlled trials. British Journal of Nutrition, 110(7), 1178-1187.
Adrianna Kalista
A graduate in clinical dietetics whose interests begin, not end, with the word diet. She has written specialist content on nutrition. She is fascinated by contemporary food culture, phytotherapy and the effects of the ketogenic diet on cognitive brain function. She promotes diet therapy and the nutritional treatment of disease.
To provide the best experiences, we use technologies like cookies to store and/or access device information. Consenting to these technologies will allow us to process data such as browsing behaviour or unique IDs on this site. Not consenting or withdrawing consent, may adversely affect certain features and functions.
Functional
Always active
The technical storage or access is strictly necessary for the legitimate purpose of enabling the use of a specific service explicitly requested by the subscriber or user, or for the sole purpose of carrying out the transmission of a communication over an electronic communications network.
Preferences
The technical storage or access is necessary for the legitimate purpose of storing preferences that are not requested by the subscriber or user.
Statistics
The technical storage or access that is used exclusively for statistical purposes.Przechowywanie techniczne lub dostęp, który jest używany wyłącznie do anonimowych celów statystycznych. Bez wezwania do sądu, dobrowolnego podporządkowania się dostawcy usług internetowych lub dodatkowych zapisów od strony trzeciej, informacje przechowywane lub pobierane wyłącznie w tym celu zwykle nie mogą być wykorzystywane do identyfikacji użytkownika.
Marketing
The technical storage or access is required to create user profiles to send advertising, or to track the user on a website or across several websites for similar marketing purposes.


 United KingdomCurrent regionDelivery within the United KingdomCurrency: Pound Sterling (£)
 GermanyDelivery within Germany and AustriaCurrency: Euro (€)
 FranceDelivery within France and BelgiumCurrency: Euro (€)
 ItalyDelivery within ItalyCurrency: Euro (€)
 PolandDelivery within Poland and EuropeCurrency: Zloty (PLN)
 Czech RepublicDelivery within the Czech Republic and SlovakiaCurrency: Czech Koruna (Kč)
 SpainDelivery within SpainCurrency: Euro (€)